

Herpesvirus infections: options and limits of systemic therapy
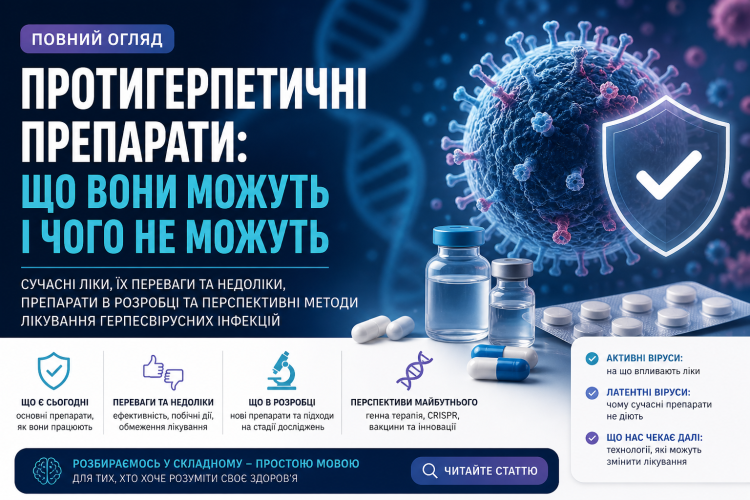
Herpesviruses—including HSV-1, HSV-2, varicella-zoster virus (VZV), Epstein–Barr virus (EBV), cytomegalovirus (CMV), HHV-6, HHV-7 and HHV-8—share an important feature: after the first infection they can remain in the body in a latent state.
Most current antivirals work best while a virus is actively replicating. They can shorten an outbreak, reduce complications and, in some situations, lower transmission risk, but they generally do not remove latent virus from nerve ganglia, lymphocytes or other reservoir cells.
Why herpesviruses are difficult to eliminate
During active infection, viral DNA is copied and new particles are produced. Drugs such as acyclovir, valacyclovir, famciclovir and ganciclovir interfere mainly with this process. During latency, these molecular targets are largely inactive. Controlling replication and eliminating a latent reservoir are therefore different goals: the first is often achievable, while the second remains a research challenge.
Antiviral medicines used today
Acyclovir, valacyclovir and famciclovir
These medicines are used mainly for HSV-1, HSV-2 and VZV. Acyclovir is well studied; valacyclovir has better oral absorption; and famciclovir is a convenient alternative in some regimens. They can treat episodes or, when clinically indicated, provide suppressive therapy. They do not eradicate latent infection, and kidney function, interactions and the clinical situation must be considered.
Topical penciclovir and docosanol
These local treatments may modestly shorten cold-sore episodes when started early. They are not systemic treatment for chronic or disseminated herpesvirus disease.
Ganciclovir and valganciclovir
These drugs are used primarily for serious CMV infection, especially in transplant medicine and severe immunosuppression; they may also be considered for severe HHV-6 disease. Bone-marrow suppression and other toxicities require medical supervision and laboratory monitoring. Valganciclovir is not simply a “stronger valacyclovir.”
Foscarnet and cidofovir
These reserve drugs may be used for severe or resistant HSV or CMV infections. Both can damage the kidneys; foscarnet can also disturb electrolytes. They require specialist care and are not routine outpatient treatments.
Letermovir and maribavir
Letermovir is used mainly to prevent CMV in selected high-risk transplant settings. Maribavir is an option for refractory or resistant post-transplant CMV. Neither is a universal drug for HSV, EBV or HHV-6/7.
Different viruses require different strategies
- HSV-1/HSV-2: acyclovir, valacyclovir or famciclovir; resistant disease may require specialist alternatives.
- VZV: acyclovir-family drugs are most useful when treatment starts early.
- CMV: ganciclovir/valganciclovir and specialist alternatives including foscarnet, cidofovir, letermovir or maribavir, depending on the indication.
- EBV: there is no standard antiviral treatment that removes latent EBV from B cells.
- HHV-6: severe disease may be treated with ganciclovir, foscarnet or cidofovir under specialist supervision.
- HHV-7: diagnosis and treatment remain less standardized.
- HHV-8: management depends on the clinical condition and often includes correction of immunosuppression rather than antivirals alone.
Promising approaches are still experimental
Helicase–primase inhibitors such as pritelivir, therapeutic vaccines, virus-specific cell therapy and CRISPR-based approaches may expand future options. Their development stage, studied population and safety differ; most are not routine treatments and should not be presented as a cure.
What not to confuse
A positive herpesvirus IgG result usually shows past exposure, not active disease and not an automatic reason for antiviral treatment. Decisions require the clinical picture and, when appropriate, PCR from the correct specimen, immune status, kidney and liver function, other conditions and the ability to monitor safety.
Do not start, stop or change antiviral treatment on your own. Ganciclovir, valganciclovir, foscarnet, cidofovir and transplant-related medicines can cause serious adverse effects and require specialist oversight.
Sources
- CDC: Genital Herpes Treatment Guidelines
- WHO guidelines for genital herpes simplex virus
- Antiviral therapies for herpesviruses
- ClinicalTrials.gov: pritelivir expanded access
This material is educational and does not replace medical assessment or individualized treatment.
 АС